
HEDIS Gap Closure for Health Plans
The last 10,000 members on your gap list aren’t going to come in.
So We Go To Them.
Principle Health Systems calls your outstanding members with care gaps, schedules them, and brings phlebotomy, laboratory testing, and diagnostic screening into their homes – at no cost to the patient – so the gaps your outreach couldn’t close still close before December 31.
Call – (832) 932-5968
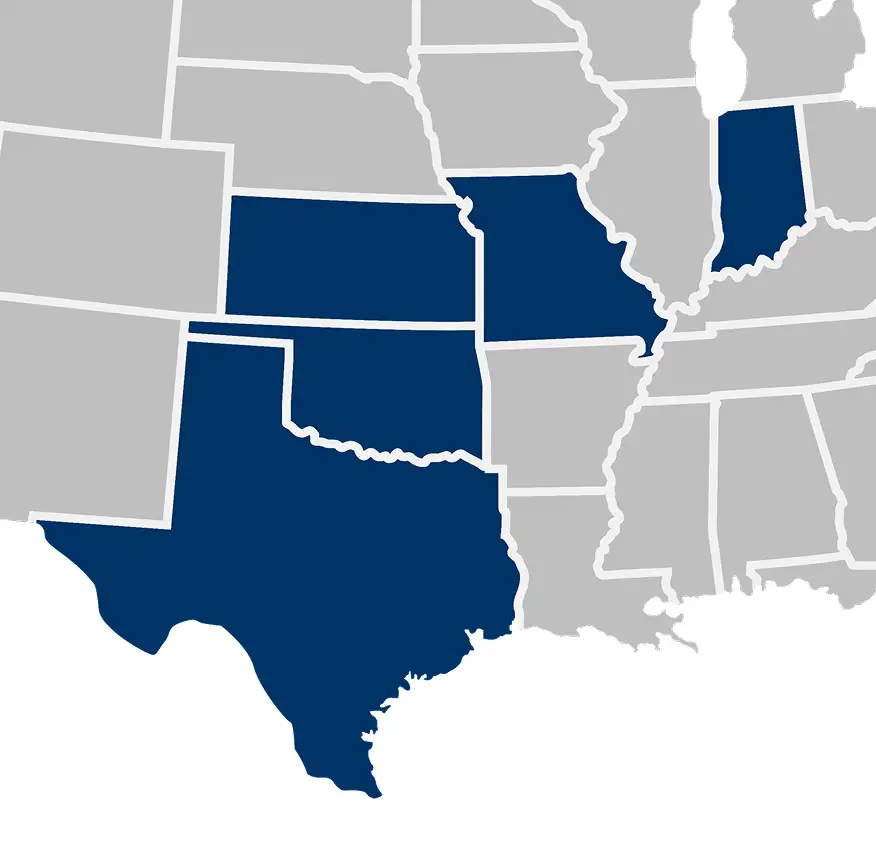
Where We Go
- Texas
- Oklahoma
- Kansas
- Indiana
- Missouri
Who We Work With
Medicare Advantage plans, Medicaid managed care organizations, D-SNPs and I-SNPs, and commercial health plans.
What Your Patients Pay
No cost to the patient, with no copay, transportation, time off work, or appointment to drive to.
You Already Know Which Members Have Open Gaps
Getting to them is the problem.
Your quality team has the list. It’s been risk-stratified, prioritized, and worked. Mailers went out. IVR ran. Care management called, twice.
And a stubborn share still hasn’t moved, because the barrier was never awareness. It’s the member who can’t drive. The member in a skilled nursing facility whose family never scheduled the follow-up. The member two hours from the nearest draw station. Or the member who is simply done with appointments.
Those members can have an outsized impact. Medicare Advantage quality bonuses turn on unforgiving thresholds. For 2026, roughly 175 MA contracts, about one-third of all contracts, landed at exactly 3.5 stars (CMS 2026 Star Ratings Fact Sheet). One tier below the bonus. In many cases, the difference comes down to a handful of measures and a few thousand members who never completed a blood draw.

The last mile of gap closure isn’t an outreach problem. It’s a logistics problem. That’s the part we solve.
HEDIS Gap Closure for Critical Diagnostics
Send Us the List. We Handle the Rest.
1. Outreach
Our full-service call center manages approximately 100,000 scheduled visits annually. We connect with members using customized talk tracks, text campaigns, text-based scheduling, AI-enabled phone systems, and follow-up outreach to help coordinate needed diagnostic services.
2. Mobile Diagnostics
Our phlebotomists and clinical staff bring eligible diagnostic services directly to members at home, in skilled nursing or assisted living facilities, and in other community settings. Services may include blood draws, urine collection, blood pressure readings, FIT kits, and imaging, all at no cost to the patient.
3. Patient Support
We help patients understand what to expect before and during their visit, answer questions, and coordinate the delivery of results back to the attributed practice. Your practices maintain the patient relationship while we help complete the diagnostic services needed to support quality gap closure.
What We Close, and What It Takes to Close It
Principle Health Systems supports diagnostic services associated with several key HEDIS measures. Here’s how our services align with the testing and documentation each measure requires.
How It Works

The Data Path
A Gap Doesn’t Close in the Living Room.
It Closes in Your Submission File.
Completing the diagnostic service is only part of gap closure. The result also needs to be delivered to your quality reporting workflow with the right data and documentation. Before services begin, we work with your quality and IT teams to establish how results will be returned, including claims and encounter data, structured supplemental data, and supporting source documentation when needed.
We also plan around the reporting deadlines for your program. Services must be completed within the measurement year, while supplemental data deadlines may come earlier than final submission dates. Through Principle Insights, your team can also track outreach, scheduling, completed services, and other program activity throughout the process. By building the data pathway, reporting, and timeline into the process from the start, we help ensure completed services can be reflected in your HEDIS reporting.
The Results
Closing more eligible gaps can help strengthen HEDIS performance and support the quality measures tied to your organization’s goals. By bringing diagnostic services directly to harder-to-reach members, Principle Health Systems helps turn outstanding care needs into completed services with results that can flow back into your quality reporting.
Principle Insights provides customized reporting throughout the process, giving your team visibility into who has been contacted, scheduled, completed services, and more. This helps your team track progress across the member population and focus follow-up efforts where they’re needed most.

Why PHS?
Your organization already has a gap closure strategy supported by analytics, member engagement, and provider outreach. Principle Health Systems complements those efforts with the outreach, mobile diagnostic services, and patient support needed to reach members who may have difficulty accessing traditional care settings.
Our capabilities bring together a full-service call center, field clinicians, laboratory testing, mobile imaging, logistics, and customized reporting through Principle Insights. By coordinating these services through one partner, we help create a more streamlined path from member outreach and scheduling to completed diagnostic services, results, and reporting.
Frequently Asked Questions
There is no cost to the patient. Services are delivered through your program, with billing arrangements established during contracting. Patients have no copay, transportation to arrange, or appointment to travel to.
Yes. In-home readings can support CBP when they meet the measure’s documentation requirements. We use validated automated devices and document the date, systolic value, and diastolic value needed for reporting.
We typically need your gap list, a secure method for data exchange, the appropriate data-sharing agreement, and coordination with your quality and IT teams on how results should be returned.
Our primary service area includes Texas, Oklahoma, Kansas, Indiana, and Missouri. Additional market coverage may also be available upon request. For organizations with broader membership footprints, we can work with your team to determine where our services can support your population.
Principle Insights provides customized reporting that gives your team visibility into member outreach, scheduling, completed services, and other program activity. Reporting can be tailored to help your team monitor progress and identify where additional follow-up may be needed.
Yes. We work with members in skilled nursing facilities, assisted living communities, long-term acute care settings, and other supported care environments in addition to private residences.
We provide disposition reporting so your team can see which members completed services, declined, could not be reached, or may require additional follow-up.
Yes. A defined member population or geographic market can be a practical way to establish workflows, evaluate results, and determine how the program could scale.
Tell us which measures you’re focused on, how many members you need to reach, and where they’re located. We’ll help determine where Principle Health Systems can support your gap closure efforts and what implementation could look like.


We Are Proud Supporters Of:


